

If you are looking into breast reconstruction in Canada, it is surgery to make the breast look and feel as natural as possible after all or part of it has been removed.
Most provincial and territorial health insurance plans cover it after breast cancer surgery, though the amount and type of coverage vary across Canada. This page is general information only, so decisions belong with your own surgeon and care team.
This page is the Canadian overview within the wider guide to breast reconstruction. It explains who provides the surgery, how coverage generally works, what choices exist, and where to read further. It is general information only, and decisions about surgery and recovery belong with the reader’s own surgeon and care team.
| Topic | What the Canadian Cancer Society says |
|---|---|
| Coverage | Most provincial and territorial plans cover it; coverage varies across Canada |
| Who does the surgery | Done by a trained plastic surgeon; may take more than one operation |
| Natural look and feel | A reconstructed breast will not look exactly like a natural breast |
| Implant lifespan | Implants may last 10 to 15 years before removal or replacement |
| Smoking and flap surgery | Strongly recommended to quit smoking at least 3 months beforehand |
These points come from the Canadian Cancer Society pages on breast reconstruction surgery and types of breast reconstruction. Information can change, so please check the sources for the latest details.
Why reconstruction matters in the Canadian context
Breast cancer is the most common cancer among women living in Canada, which explains why questions about what comes after surgery are so widespread. The Canadian Cancer Society estimates that 32,400 women in Canada will be diagnosed with breast cancer in 2026, representing 26% of all new cancer cases in women. On average, 89 women a day receive that diagnosis. The same page estimates that about 1 in 8 women in Canada will develop breast cancer during their lifetime. A fuller look at the numbers, including trends and mortality, is in the page on breast cancer statistics Canada.
Not everyone who has a mastectomy or breast-conserving surgery chooses reconstruction, and not every person is a candidate. The Canadian Cancer Society is clear that having breast reconstruction or wearing a breast prosthesis is not medically necessary. It also notes that for people who are struggling with the loss of a breast and changes to appearance, these options may help them feel more like themselves. The choice is personal, and it is built on what feels most comfortable and confident for the individual and on what the surgeon says is possible.
Understanding how a diagnosis is reached also helps put the later decisions in order. Screening programs are run by provinces and territories, and the page on breast cancer screening Canada explains how they work. For example, the Canadian Cancer Society advises that people aged 40 to 74 have a mammogram every 2 years, and it adds that not every province or territory offers mammograms through an organized program for people in their 40s.

What reconstruction involves
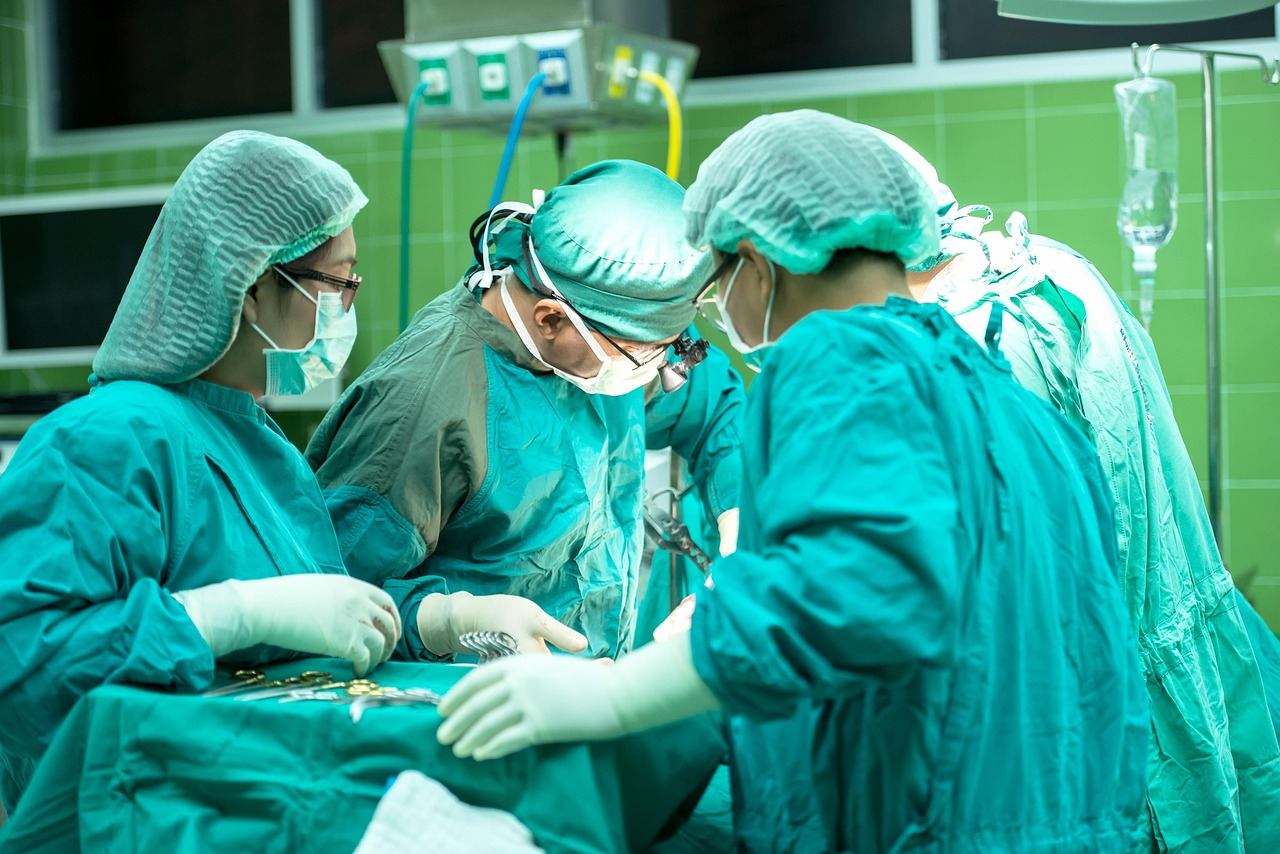
The Canadian Cancer Society describes breast reconstruction as surgery to make the breast look and feel as natural as possible after all or part of it has been removed. It is done by a plastic surgeon who is specially trained to do this surgery, and it may require more than one operation.
Expectations matter here. The same source states that a reconstructed breast will not look exactly like a natural breast, and that it will never feel exactly like one in terms of sensation and firmness.
The surgeon weighs several factors when deciding which types of reconstruction to offer. They include overall health and any health problems, the health of the tissue where the reconstruction will be done, whether radiation therapy or chemotherapy has been or will be given, how much tissue was removed, the amount of muscle and fat available in the abdomen, thigh, back or buttock, the shape and size of both breasts, and personal preferences. How these influence the choice is also covered in the page on life after breast cancer surgery.
Main types of reconstruction offered
According to the Canadian Cancer Society, the types that may be offered are breast implants, autologous breast reconstruction and nipple and areola reconstruction. Each has its own preparation, recovery pattern and set of possible complications.
Because the three types differ so much, the conversation with the surgeon usually starts with the person’s priorities. The Canadian Cancer Society also notes that, for people with larger breasts, surgery on the other, unaffected breast may be part of the plan so that the two sides look balanced. None of these priorities is more correct than another, and the surgeon can explain which are realistic given the person’s health and treatment history.
Implants
A breast implant is a round sac made of rubberized silicone, filled with sterile salt water (saline) or silicone gel. The same page says that silicone implants are most commonly used in Canada. Tissue expansion, where an expander is gradually filled over several visits before the permanent implant is placed, is one approach, and direct-to-implant reconstruction using an acellular dermal matrix is another. The page notes that the direct approach may not be available everywhere in Canada, which is one example of regional variation in access.
The possible side effects and complications of implant surgery, as listed by the Canadian Cancer Society, are infection, a buildup of fluid called seroma, pain, scar tissue around the implant called capsular contracture, which can make the breast feel hard and lose its shape, movement of the implant, wrinkling, and leaking or breaking of the implant. The page adds that people should tell the healthcare team about any problem they think comes from the surgery, because the sooner they report problems, the sooner the team can suggest ways to help. After an implant is removed, changes such as dimpling, puckering or wrinkling of the skin may appear where the implant was.
Implants are not permanent. The Canadian Cancer Society says that breast implants may last 10 to 15 years before they need to be removed or replaced, and that the risk of rupture increases as an implant gets older. If radiation therapy has been given to the chest, the surgeon may not recommend implants because of a greater chance of complications.
Using the body’s own tissue
Autologous reconstruction uses skin, fat and sometimes muscle from other parts of the body. The tissue, called a flap, is usually taken from the abdomen, but it can also come from the back, buttock or thigh. A free flap is completely detached from its blood supply and reattached in the chest, while a pedicle flap stays attached to its original blood supply. The Canadian Cancer Society states that the reconstructed breast has a more natural feel than a breast implant.
Smoking matters for this type of surgery. The Canadian Cancer Society says that people who smoke are strongly recommended to quit at least 3 months before autologous breast reconstruction, because smoking affects blood flow to the skin and underlying tissues.
Autologous surgery carries its own list of possible effects. The Canadian Cancer Society names infection, bleeding, fluid buildup where the tissue was taken, scars at the donor area, breasts that are not the same size or shape, weakness and bulging of the abdominal muscles when muscle has been removed, a slightly different colour and texture of the rebuilt breast compared with the surrounding area, and less muscle strength in the back if tissue came from there. It adds that people with larger breasts or earlier radiation therapy to the chest may have more complications. These lists are not meant to alarm. They are the topics that surgeons are expected to cover before any decision, so that the person understands both sides of the choice.
Nipple and areola reconstruction
If the nipple and areola were removed during a mastectomy, they can be rebuilt as the final step of reconstruction. The Canadian Cancer Society notes this is done after the reconstructed breast has fully healed, at least 3 to 6 months after breast reconstruction surgery.
Details of the approach, including how the tissue is obtained, are described in the source page, and the surgeon can explain how each option would apply after a particular mastectomy.
Timing of reconstruction
When reconstruction happens depends on which cancer treatments are needed and on when the person feels ready. The table below sets out the three timing approaches described by the Canadian Cancer Society.
| Approach | When it happens |
|---|---|
| Immediate | At the same time as surgery to remove part or all of the breast |
| Delayed | As a separate surgery after other cancer treatments, including chemotherapy and radiation therapy, are finished |
| Immediate-delayed | A tissue expander is placed during cancer surgery, and the reconstruction is completed after other treatments are finished |
The table follows the Canadian Cancer Society’s page on breast reconstruction surgery, which also says that delayed reconstruction recommended by a surgeon may be done 6 to 12 months after a mastectomy or breast-conserving surgery, and can be done years after treatment.
Immediate reconstruction is not always offered. A person who still needs chemotherapy and radiation therapy may not be offered it, because those treatments could damage the reconstructed breast and raise the risk of complications such as problems healing and infections. Someone who is not ready for more surgery can choose to remain flat or try a prosthesis before deciding, and can ask the surgeon about delaying reconstruction until the time is right.
Timing is also a matter of readiness rather than only of cancer treatment. The Canadian Cancer Society observes that a person may not be ready for more surgery, may not want to face the risks that come with it, or may feel unsure about reconstruction at all. Waiting does not close the door, and the care team can revisit the question later. People who do not know what they want in the days after a diagnosis often find it helps to separate the decision about cancer treatment from the decision about reconstruction, and to give themselves time to learn about each option.
Coverage, costs and follow-up
Health coverage is a central question for people in Canada. The Canadian Cancer Society states that breast reconstruction after breast cancer surgery is covered by most provincial and territorial health insurance plans, while the amount and type of coverage vary across Canada, and it advises checking the provincial or territorial plan before surgery. The page on breast reconstruction coverage in Canada goes into this in more detail, and the page on breast reconstruction wait times Canada looks at timing and access.
In the context of remaining flat, the Canadian Cancer Society points out that there may be additional costs for mastectomy bras and new prostheses over time that are not covered by government or private insurance plans. For prostheses it also says that the cost of a permanent prosthesis may be covered by a provincial or territorial health insurance plan, and most personal or work health insurance plans will cover at least part of the cost.
Follow-up is part of care after reconstruction. Depending on the type, the Canadian Cancer Society says visits may be each week or month during the first year, becoming less frequent as the body heals. People with implants or autologous reconstruction do not need regular mammography on the reconstructed breast, but they still need it on the natural breast.
The Canadian Cancer Society also encourages people to know what is normal for both the natural and the reconstructed breast, and to report changes such as fluid leaking from the breast, swelling or new skin changes. It says it may take several months for tissue to heal and become soft after reconstruction, and that scars fade over time but might never go away completely. A bra can be worn once the incision has completely healed. Advice on returning to normal activities and exercise comes from the surgeon, who knows the type of operation that was done.
Surgeons and safety
Reconstruction is performed by a surgeon with specific training, and the Canadian pathway to that training is explained in the page on how to find a plastic surgeon in Canada. The Canadian Cancer Society advises talking with the surgeon about hopes for the surgery before any decision is made, and about when normal activities and exercise can resume.
Questions worth bringing to a consultation follow from the factors above. Writing the answers down, and bringing a family member or friend to the appointment, can make the information easier to recall later. The surgeon and the wider care team remain the right people to answer questions that depend on individual health.
Implant safety is regulated nationally. The Canadian Cancer Society reports that, in very rare cases, people with silicone gel or saline implants can develop a type of non-Hodgkin lymphoma called breast implant-associated anaplastic large-cell lymphoma, and that in 2019 Health Canada suspended the medical licence for the one brand of textured breast implants that were available in Canada. More on the regulator’s position is on the page about breast implant safety Canada.

Other paths and sources of support
Reconstruction is one of several paths after surgery. A breast prosthesis is an artificial breast form worn inside a bra, and the Canadian Cancer Society says a person may want to wear one while unsure about reconstruction or while waiting for surgery. Remaining flat means having neither reconstruction nor a prosthesis. According to the Canadian Cancer Society, many people choose to remain flat because they are comfortable and confident with their body as it is, and there is no single right choice.
The reasons people give for remaining flat are varied. The Canadian Cancer Society lists that reconstruction means more surgery, that other health issues such as diabetes or heart disease may add risk, that a person may not want the possible complications, and that a person may not want implants or tissue taken from elsewhere in the body. It also says that many people are happy with their breast reconstruction, but a reconstructed breast does not feel completely natural. Both statements can be true, and neither decision is final in every case.
Talking with the healthcare team, family, friends and people who have been through the same experience can help. Organizations across the country offer that kind of connection, and the page on breast cancer support Canada describes them. The wider recovery picture, including health and wellbeing after surgery, is covered in the wider recovery guide on this site.
Frequently asked questions
Is breast reconstruction covered by health plans in Canada?
Show answer
Most provincial and territorial plans cover it after breast cancer surgery, according to the Canadian Cancer Society, but the amount and type of coverage differ by region.
Who performs the surgery?
Show answer
A plastic surgeon with specialized training in this surgery performs it, and the care team plans the options with each person.
Is reconstruction required after a mastectomy?
Show answer
No.
Can reconstruction happen at a later date?
Show answer
Yes. Delayed reconstruction can be done after other treatments finish, including years later if that suits the person.
What other costs should be considered?
Show answer
Mastectomy bras and replacement prostheses may carry costs that public and private plans do not always cover, so checking the plan beforehand is useful.


